
Council Agenda item 13A
Employee Health Insurance Benefits for Fiscal Year 2026/2027. (Roll Call)
City Council, Monday, June 22, 2026
Download these 13 pages, 1.3 MB Whole packet, 65 pages, 6.4 MB
Page 27

Text of page 27
City Council Agenda Item Report FROM:
Ryan Cummins, City Manager Nicole Bredeweg, Treasurer/Finance Officer
MEETING DATE:
June 22, 2026
SUBJECT:
Employee Health Insurance Benefits for FY 26-27
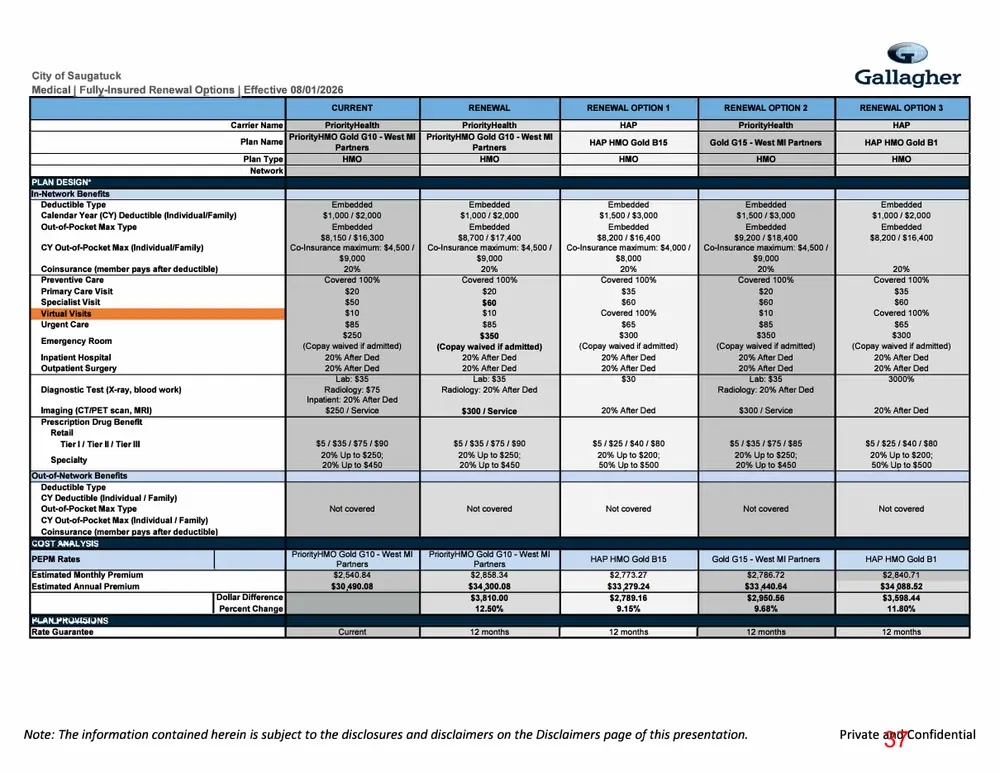
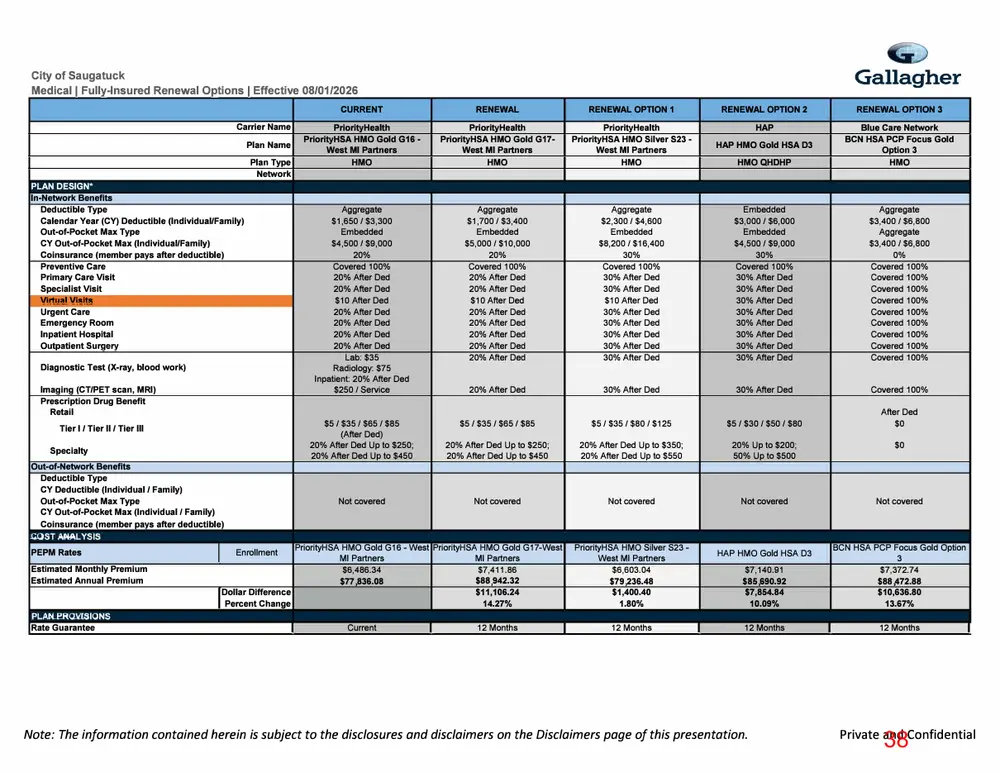
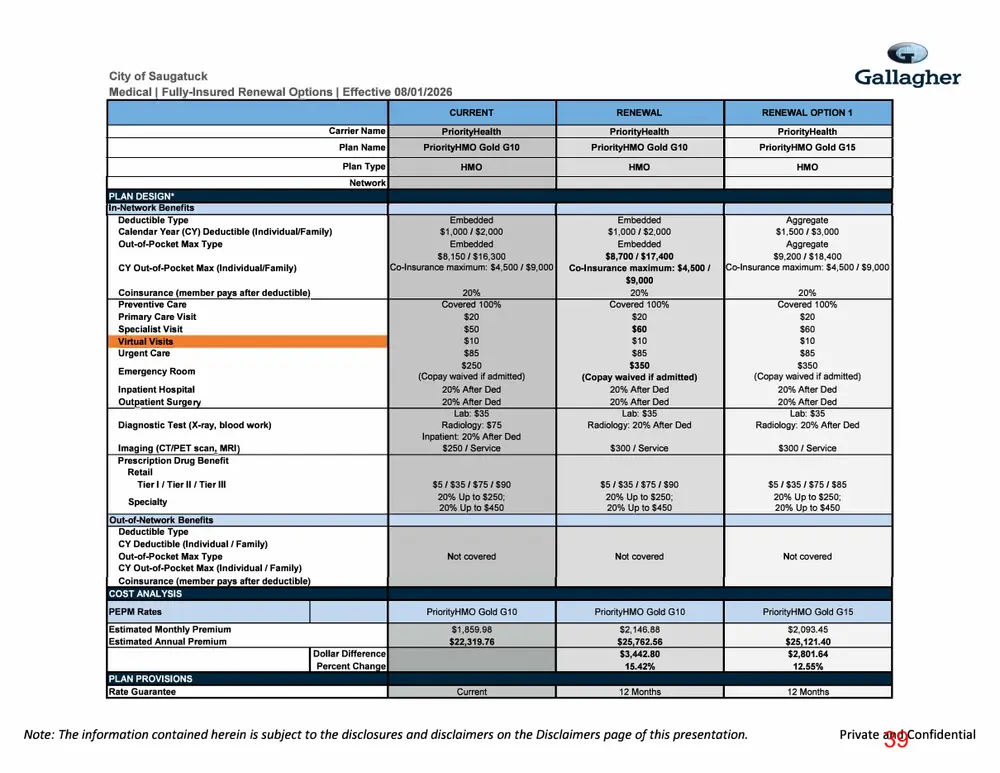
DESCRIPTION: The City’s employee health insurance agent, Gallagher Benefit Services LLC, has provided renewal information and plan options for employee health insurance coverage for the upcoming fiscal year. The quote to renew the City’s current Priority Health plans would result in an 11.91% increase, which equates to an annual increase of $18,359.04. Total annual premium would increase from $154,145.92 to $172,504.96. The City currently offers multiple Priority Health plan options, including both traditional HMO and high-deductible HSA-qualified plans. Staff reviewed the renewal information and evaluated the available options, including the impact to the City, the impact to employees, plan design changes, deductible and out-of-pocket exposure, prescription coverage, and overall competitiveness of the City’s benefits package. The City currently pays 100% of the employee premium for health insurance. This benefit remains an important part of the City’s employee retention and recruitment strategy, particularly in a competitive municipal employment environment. REVIEW PROCESS Staff reviewed the renewal options and compared the available plans against the City’s current employee needs and overall benefit structure. In staff’s opinion, while cost savings were considered, the available alternatives did not provide enough savings to justify significant disruption to employees or a major reduction in the City’s benefit offering.
Page 28

Text of page 28
Staff also reviewed the City’s Health Savings Account contribution for employees enrolled in the high-deductible health plan. The City currently contributes $2,500 annually to eligible employee HSAs. In order to maintain the value of this benefit and help offset employee exposure under the high-deductible plan, staff recommends increasing the City’s annual HSA contribution to $2,600. RECOMMENDATION Staff recommends renewing the City’s employee health insurance coverage as presented and increasing the City’s annual HSA contribution from $2,500 to $2,600 for eligible employees enrolled in the high-deductible health plan. BUDGET ACTION: None at this time. LEGAL REVIEW: None at this time. SAMPLE MOTION: Motion to approve the employee health insurance renewal as presented and to increase the City’s annual Health Savings Account contribution for eligible employees enrolled in the highdeductible health plan from $2,500 to $2,600 for FY 26-27.
Page 2
Page 29

Text of page 29
2026 - 2027
Health Insurance Recommendation
Nicole Bredeweg PRESENTATION TITLE
1 29
Page 30

Text of page 30
EMPLOYEE HEALTH INSURANCE RENEWAL FY 2026-2027 RECOMMENDATION: • Renew the existing employee health insurance plan structure. • Continue offering both low-deductible and HSA-eligible plan options. • Increase the City’s annual HSA contribution from $2,500 to $2,600. Last year was the larger decision point. This year’s recommendation is to maintain the structure that was put in place and avoid unnecessary disruption to employees.
6/18/2026
Page 31

Text of page 31
WHAT CHANGED LAST YEAR FY 2025-2026 PLAN STRUCTURE:
• The City moved from the prior plan structure to a menu of options. • Employees in partner counties were offered West Michigan Partners plan options. • Employees outside partner counties were offered non-partner plan options. • HSA-eligible high-deductible options were added. • The goal was to manage cost increases while preserving competitive benefits. Last year’s change helped reduce the projected cost increase while maintaining strong employee benefits. It also gave employees more 3 choice based on their own needs. 31
6/18/2026
Page 32

Text of page 32
CURRENT EMPLOYEE ELECTIONS: • 2 employees: low-deductible West Michigan Partners • 1 employee: low-deductible non-West Michigan Partners • 7 employees: high-deductible West Michigan Partners • 2 employees: waived coverage
The elections show that the plan menu is being used in a balanced way. Most employees selected the HSA-eligible plan, but the lowerdeductible options remain important for employees whose circumstances make that plan a better fit.
6/18/2026
Page 33

Text of page 33
REVIEW PROCESS: • Compared plan offerings for both City cost and employee impact • Evaluated whether changes to the current plan structure would produce meaningful savings • Considered whether potential savings justified employee disruption • Determined that renewal of the existing plan structure best balances cost control, employee choice, and benefit stability
6/18/2026
Page 34

Text of page 34
RECOMMENDATION: • Renew existing plan offerings. • Maintain benefit stability for employees. • Support retention and recruitment. • Avoid unnecessary annual disruption. • Budget includes the anticipated increase. • Increase HSA contribution from $2,500 to $2,600 to offset the increase in deductible.
6/18/2026
Page 35

Text of page 35
CONCLUSION: The recommendation this year is not to make another major structural change. Last year, the City made the larger adjustment to its health insurance offerings in order to manage cost increases while still providing a competitive benefit package. This year, staff is recommending renewal of that same structure. Maintaining the current plan options supports employee retention, reduces disruption, and helps preserve trust in the City’s benefit offerings. The proposed HSA contribution increase is modest and is intended to help offset the deductible increase for employees who selected the highdeductible plan.
6/18/2026
Page 36

Text of page 36
Any questions?
6/18/2026
Page 37
Text of page 37
Gallagher
City of Saugatuck Medical I Fully-Insured Renewal Options I Effective 08/01/2026 RENEWAL
RENEWAL OPTION 1
RENEWAL OPTION 2
PriorityHealth PriorityHMO Gold G10 • West Ml Plan Name Partners Plan Type HMO Network
CURRENT
PriorityHealth PriorityHMO Gold G10 • West Ml Partners HMO
HAP
PriorityHealth
HAP
HAP HMO Gold B15
Gold G15 • West Ml Partners
HAP HMO Gold B1
HMO
HMO
HMO
Embedded $1,000 I $2,000 Embedded $8,150/$16,300 Co-Insurance maximum:$4,500/ $9,000 20% Covered 100% $20 $50 $10 $85 $250 (Copay waived if admitted) 20%AfterDed 20%AfterDed Lab:$35 Radiology:$75 Inpatient: 20%AfterDed $250 I Service
Embedded $1,000 I $2,000 Embedded $8,700 I $17,400 Co-Insurance maximum:$4,500/ $9,000 20% Covered 100% $20 $60 $10 $85 $350 (Copay waived if admitted) 20%AfterDed 20%AfterDed Lab:$35 Radiology: 20%AfterDed
Embedded $1,500/$3,000 Embedded $8,200 I $16,400 Co-Insurance maximum:$4,000 I $8,000 20% Covered 100% $35 $60 Covered 100% $65 $300 (Copay waived if admitted) 20%AfterDed 20%AfterDed $30
Embedded $1,500/$3,000 Embedded $9,200 I $18,400 Co-Insurance maximum:$4,500/ $9,000 20% Covered 100% $20 $60 $10 $85 $350 (Copay waived if admitted) 20%AfterDed 20%AfterDed Lab:$35 Radiology: 20%AfterDed
Embedded $1,000 I $2,000 Embedded $8,200 I $16,400
$300 / Service
20%AfterDed
$300 I Service
20%AfterDed
$5/$35/$75/$90 20% Up to $250; 20% UD to $450
$5/$35/$75/$90 20% Up to $250; 20% UD to $450
$5/$25/$40/$80 20% Up to $200; 50% UD to $500
$5/$35/$75/$85 20% Up to $250; 20% UD to $450
$5/$25/$40/$80 20% Up to $200; 50% UD to $500
Not covered
Not covered
Not covered
Not covered
Not covered
PriorityHMO Gold G10 • West Ml Partners $2,540.84 $30 490.08
PriorityHMO Gold G10 • West Ml Partners $2,858.34 $34 300.08 $3,810.00 12.50%
HAP HMO Gold 815
Gold G15 - West Ml Partners
HAP HMO Gold 81
$2,773.27 $33 279.24 $2,789.16 9.15%
$2,786.72 $33 440.64 $2,950.56 9.68%
$2,840.71 $34 088.52 $3,598.44 11.80%
Current
12 months
12 months
12 months
Carrier Name
PLAN DESIGN* In-Network Benefits Deductible Type Calendar Year (CY) Deductible (Individual/Family) Out-of-Pocket Max Type CY Out-of-Pocket Max (Individual/Family) Coinsurance (member pays after deductible) Preventive Care Primary Care Visit Specialist Visit Virtual Vlsllll Urgent Care Emergency Room Inpatient Hospital Outpatient Surgery Diagnostic Test (X-ray, blood work) Imaging (CT/PET scan, MRI) Prescription Drug Benefit Retail Tier I / Tier II / Tier Ill Specialty Out-of-Network Benefits Deductible Type CY Deductible (Individual / Family) Out-of-Pocket Max Type CY Out-of-Pocket Max (Individual / Family) Coinsurance lmember oavs after deductible)
PEPM Rates Estimated Monthly Premium Estimated Annual Premium
Dollar Difference Percent Change
•..1•, •■• • tn•r..., I
Rate Guarantee
12 months
Note: The information contained herein is subject to the disclosures and disclaimers on the Disclaimers page of this presentation.
RENEWAL OPTION 3
20% Covered 100% $35 $60 Covered 100% $65 $300 (Copay waived if admitted) 20%AfterDed 20%AfterDed 3000%
Private and Confidential
Page 38
Text of page 38
Gallagher
City of Saugatuck Medical I Fully-Insured Renewal Options I Effective 08/01/2026 Carrier Name Plan Name Plan Type Network PLAN DESIGN* In-Network Benefits Deductible Type Calendar Year (CY) Deductible (Individual/Family) Out-of-Pocket Max Type CY Out-of-Pocket Max (Individual/Family) Coinsurance (member pays after deductible) Preventive Care Primary Care Visit Specialist Visit
\11,tnal\ll■lta
Urgent Care Emergency Room Inpatient Hospital Outpatient Surqerv Diagnostic Test (X-ray, blood work) lmaaina (CT/PET scan, MRI) Prescription Drug Benefit Retail Tier I / Tier II / Tier Ill Specialty
Out-of-Network Benefits Deductible Type CY Deductible (Individual / Family) Out-of-Pocket Max Type CY Out-of-Pocket Max (Individual / Family) Coinsurance (member pays after deductible)
PEPM Rates Estimated Monthly Premium Estimated Annual Premium
•I••■�• ,._,.,.., I Rate Guarantee
CURRENT
RENEWAL
RENEWAL OPTION 1
RENEWAL OPTION 2
RENEWAL OPTION 3
PriorityHealth PriorityHSA HMO Gold G16 West Ml Partners HMO
PriorityHealth PriorityHSA HMO Gold G17West Ml Partners HMO
PriorityHealth PriorityHSA HMO Silver S23 West Ml Partners HMO
HAP HAP HMO Gold HSA DJ HMOQHDHP
Blue Care Network BCN HSA PCP Focus Gold Option 3 HMO
Aggregate $1,650 / $3,300 Embedded $4,500 I $9,000 20% Covered 100% 20% AfterDed 20% AfterDed $10 AfterDed 20% AfterDed 20% AfterDed 20% AfterDed 20% AfterDed Lab:$35 Radiology:$75 Inpatient: 20% AfterDed $250 I Service
Aggregate $1,700 I $3,400 Embedded $5,000 I $10,000 20% Covered 100% 20% AfterDed 20% AfterDed $1o AfterDed 20% AfterDed 20% AfterDed 20% AfterDed 20% AfterDed 20% AfterDed
Aggregate $2,300 I $4,600 Embedded $8,200 I $16,400 30% Covered 100% 30% AfterDed 30% AfterDed $10 AfterDed 30% AfterDed 30% AfterDed 30% AfterDed 30% AfterDed 30% AfterDed
Embedded $3,000 I $6,000 Embedded $4,500 I $9,000 30% Covered 100% 30% AfterDed 30% AfterDed 30% AfterDed 30% AfterDed 30% AfterDed 30% AfterDed 30% AfterDed 30% AfterDed
Aggregate $3,400 I $6,800 Aggregate $3,400 I $6,800 0% Covered 100% Covered 100% Covered 100% Covered 100% Covered 100% Covered 100% Covered 100% Covered 100% Covered 100%
20% AfterDed
30% AfterDed
30% AfterDed
Covered 100%
$5 / $35 / $65 / $85 (AfterDed) 20% AfterDed Up to $250; 20% AfterDed Up to $450
$5 / $35 / $65 / $85
$5 / $35 / $80 / $125
$5 / $30 / $50 / $80
AfterDed $0
20% AfterDed Up to $250; 20% AfterDed Up to $450
20% AfterDed Up to $350; 20% AfterDed Up to $550
20% Up to $200; 50% Up to $500
Not covered
Not covered
Not covered
Not covered
Not covered
PriorityHSA HMO Gold G16 - West PriorityHSA HMO Gold G17-West Ml Partners Ml Partners $6,486.34 $7,411.86 $88 942.32 $77 836.08 Dollar Difference $11,106.24 Percent Change 14.27% Enrollment
Current
12 Months
PriorityHSA HMO Silver S23 West Ml Partners $6,603.04 $79 236.48 $1,400.40 1.80% 12 Months
BCN HSA PCP Focus Gold Option 3 $7,372.74 $88 472.88 $10,636.80 13.67%
HAP HMO Gold HSA 03 $7,140.91 $85 690.92 $7,854.84 10.09%
12 Months
Note: The information contained herein is subject to the disclosures and disclaimers on the Disclaimers page of this presentation.
12 Months
Private and Confidential
Page 39
Text of page 39
Gallagher
City of Saugatuck Medical I Fully-Insured Renewal O�tions I Effective 08/01/2026 CURRENT
RENEWAL
RENEWAL OPTION 1
Carrier Name
Priori!}t_Health
Priori!}t_Health
Priori!}t_Health
Plan Name
PriorityHMO Gold G10
PriorityHMO Gold G10
PriorityHMO Gold G15
Plan Type
HMO
HMO
HMO
Embedded $1,000 I $2,000 Embedded $8,150 / $16,300 Co-Insurance maximum:$4,500 I $9,000
Embedded $1,000 I $2,000 Embedded $8,700 I $17,400 Co-Insurance maximum: $4,500 / $9,000 20% Covered 100% $20 $60 $10 $85 $350 (Copay waived if admitted) 20% After Ded 20% After Ded Lab:$35 Radiology: 20% After Ded
Aggregate $1,500 / $3,000 Aggregate $9,200 I $18,400 Co-Insurance maximum:$4,500 I $9,000
$300 I Service
$300 I Service
$5 / $35 / $75 / $90 20% Up to $250; 20% Up to $450
$5 / $35 / $75 / $90 20% Up to $250; 20% Up to $450
$5 / $35 / $75 / $85 20% Up to $250; 20% Up to $450
Not covered
Not covered
Not covered
Network In-Network Benefits Deductible Type Calendar Year (CY) Deductible (Individual/Family) Out-of-Pocket Max Type CY Out-of-Pocket Max (Individual/Family) Coinsurance (member pays after deductible) Preventive Care Primary Care Visit S_!)_ecialist Visit
Vlrtual Visits Urgent Care
Emergency Room Inpatient Hospital Outeatient Surge Diagnostic Test (X-ray, blood work) Imaging (CT/PET scan! MRI Prescription Drug Benefit Retail Tier I / Tier II / Tier Ill Specialty Out-of-Network Benefits Deductible Type CY Deductible (Individual / Family) Out-of-Pocket Max Type CY Out-of-Pocket Max (Individual / Family)
20% Covered 100% $20 $50 $10 $85 $250 (Copay waived if admitted) 20% After Ded 20% After Ded Lab:$35 Radiology:$75 Inpatient: 20% After Ded $250 / Service
Note: The information contained herein is subject to the disclosures and disclaimers on the Disclaimers page of this presentation.
20% Covered 100% $20 $60 $10 $85 $350 (Copay waived if admitted) 20% After Ded 20% After Ded Lab:$35 Radiology: 20% After Ded
Private and Confidential