
Workshop Agenda item 6C
Employee Health Insurance Benefits
City Council Workshop, Wednesday, June 18, 2025
Download these 3 pages, 1.5 MB Whole packet, 72 pages, 7.7 MB
Page 44

Text of page 44
City Council Agenda Item Report FROM:
Ryan Cummins, City Manager
MEETING DATE:
June 18, 2025
SUBJECT:
Employee Health Insurance Benefits for FY 25-26
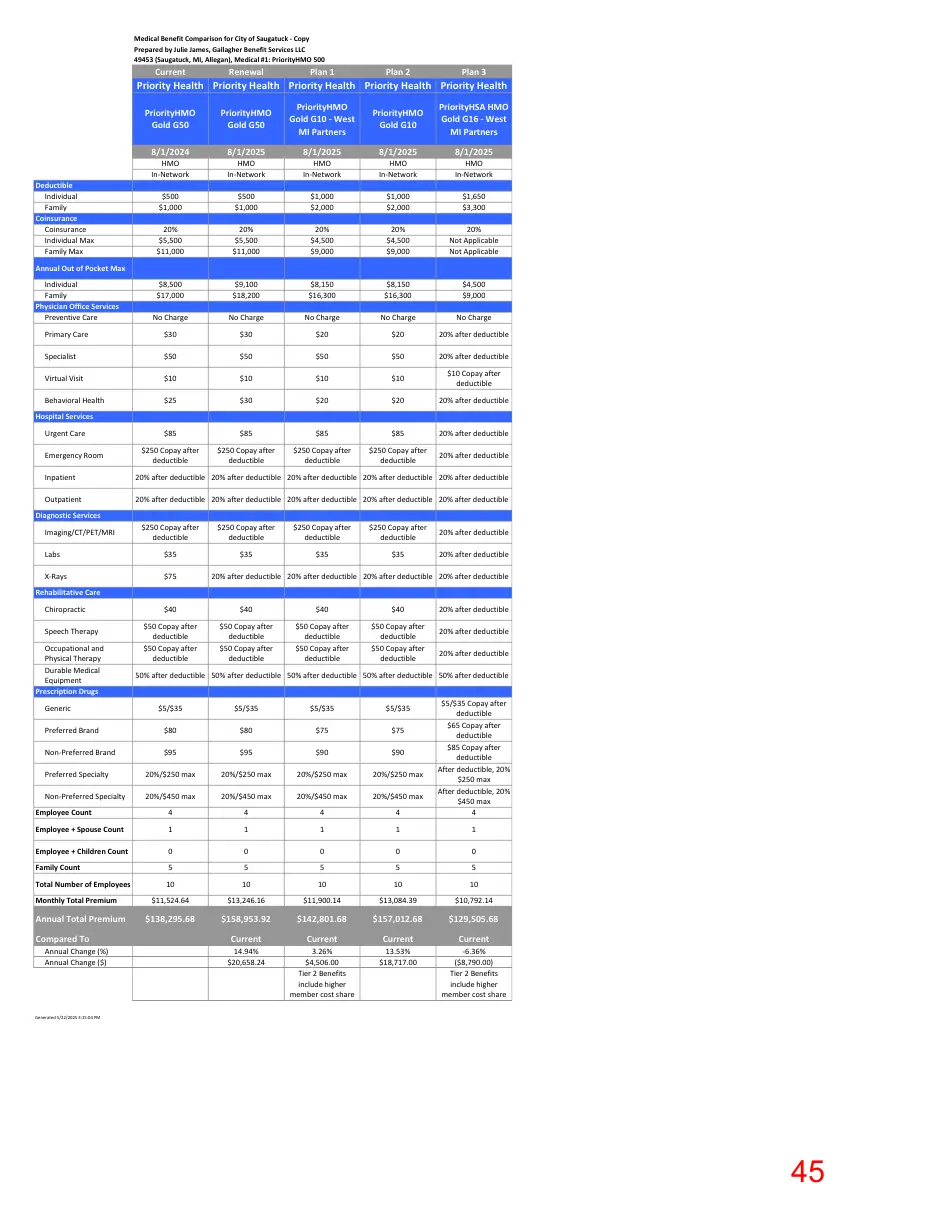
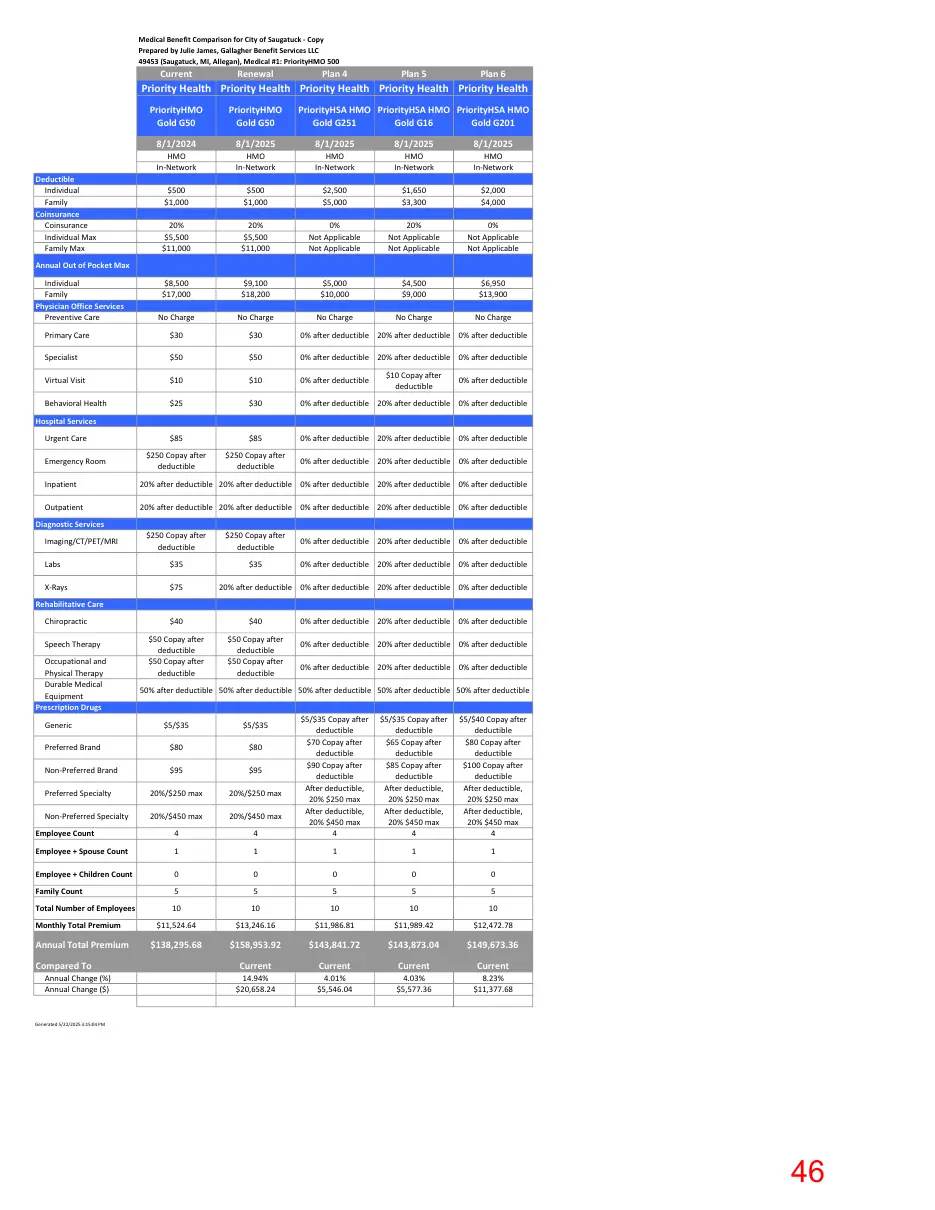
DESCRIPTION: The City’s employee health insurance agent, Gallagher Benefit Services LLC (Gallagher), has provided the attached quotes for coverage for next fiscal year. The quote to renew the existing Priority Health HMO plan will result in a 14.94% increase, which equates to an annual change of $20,658.24. We aren’t alone in seeing significant percentage increases. State regulators approved the rate changes. Saugatuck Township’s quote showed their current plan increasing 13.2%. Fennville’s quote was a 14.3% increase. Kalamazoo Lake Sewer-Water Authority’s quote also showed an increase of 12.7%. The City Treasurer/Finance Officer and I have been meeting with Gallagher to discuss options to lessen our cost increase. We have also been comparing our existing benefits against nearby municipalities and running numbers on various options. At the workshop meeting, we will have a presentation on the recommendation for next fiscal year. BUDGET ACTION: None at this time. LEGAL REVIEW: Legal will be at your meeting for any questions you may have. SAMPLE MOTION: Workshop item.
Page 45
Text of page 45
Medical Benefit Comparison for City of Saugatuck - Copy Prepared by Julie James, Gallagher Benefit Services LLC 49453 (Saugatuck, MI, Allegan), Medical #1: PriorityHMO 500
Current
Renewal
Plan 1
Plan 2
Plan 3
Priority Health Priority Health Priority Health Priority Health Priority Health
Deductible Individual Family Coinsurance Coinsurance Individual Max Family Max
PriorityHMO Gold G50
PriorityHMO Gold G50
PriorityHMO Gold G10 - West MI Partners
PriorityHMO Gold G10
PriorityHSA HMO Gold G16 - West MI Partners
8/1/2024
8/1/2025
8/1/2025
8/1/2025
8/1/2025
HMO In-Network
HMO In-Network
HMO In-Network
HMO In-Network
HMO In-Network
$500 $1,000
$500 $1,000
$1,000 $2,000
$1,000 $2,000
$1,650 $3,300
20% $5,500 $11,000
20% $5,500 $11,000
20% $4,500 $9,000
20% $4,500 $9,000
20% Not Applicable Not Applicable
$8,500 $17,000
$9,100 $18,200
$8,150 $16,300
$8,150 $16,300
$4,500 $9,000
Annual Out of Pocket Max Individual Family Physician Office Services Preventive Care
No Charge
No Charge
No Charge
No Charge
No Charge
Primary Care
$30
$30
$20
$20
20% after deductible
Specialist
$50
$50
$50
$50
20% after deductible
Virtual Visit
$10
$10
$10
$10
$10 Copay after deductible
Behavioral Health
$25
$30
$20
$20
20% after deductible
Hospital Services
Urgent Care Emergency Room
$85
$85
$85
$85
20% after deductible
$250 Copay after deductible
$250 Copay after deductible
$250 Copay after deductible
$250 Copay after deductible
20% after deductible
Inpatient
20% after deductible 20% after deductible 20% after deductible 20% after deductible 20% after deductible
Outpatient
20% after deductible 20% after deductible 20% after deductible 20% after deductible 20% after deductible
Diagnostic Services
Imaging/CT/PET/MRI
$250 Copay after deductible
Labs
$35
X-Rays
$75
$250 Copay after deductible
$250 Copay after deductible
$250 Copay after deductible
20% after deductible
$35
$35
$35
20% after deductible
20% after deductible 20% after deductible 20% after deductible 20% after deductible
Rehabilitative Care
Chiropractic Speech Therapy Occupational and Physical Therapy Durable Medical Equipment Prescription Drugs Generic
$40
$40
$40
$40
$50 Copay after deductible $50 Copay after deductible
$50 Copay after deductible $50 Copay after deductible
$50 Copay after deductible $50 Copay after deductible
$50 Copay after deductible $50 Copay after deductible
20% after deductible 20% after deductible 20% after deductible
50% after deductible 50% after deductible 50% after deductible 50% after deductible 50% after deductible
$5/$35
$5/$35
$5/$35
$5/$35
Preferred Brand
$80
$80
$75
$75
Non-Preferred Brand
$95
$95
$90
$90
$5/$35 Copay after deductible $65 Copay after deductible $85 Copay after deductible After deductible, 20% $250 max After deductible, 20% $450 max 4
Preferred Specialty
20%/$250 max
20%/$250 max
20%/$250 max
20%/$250 max
Non-Preferred Specialty
20%/$450 max
20%/$450 max
20%/$450 max
20%/$450 max
Employee Count
Employee + Spouse Count
Employee + Children Count
Family Count
Total Number of Employees
Monthly Total Premium
$11,524.64
$13,246.16
$11,900.14
$13,084.39
$10,792.14
Annual Total Premium
$138,295.68
$158,953.92
$142,801.68
$157,012.68
$129,505.68
Current
Current
Current
Current
14.94% $20,658.24
3.26% $4,506.00 Tier 2 Benefits include higher member cost share
13.53% $18,717.00
-6.36% ($8,790.00) Tier 2 Benefits include higher member cost share
Compared To Annual Change (%) Annual Change ($)
Generated 5/22/2025 3:15:04 PM
Page 46
Text of page 46
Medical Benefit Comparison for City of Saugatuck - Copy Prepared by Julie James, Gallagher Benefit Services LLC 49453 (Saugatuck, MI, Allegan), Medical #1: PriorityHMO 500
Current
Renewal
Plan 4
Plan 5
Plan 6
Priority Health Priority Health Priority Health Priority Health Priority Health PriorityHMO Gold G50
PriorityHMO Gold G50
8/1/2024
8/1/2025
8/1/2025
8/1/2025
8/1/2025
HMO In-Network
HMO In-Network
HMO In-Network
HMO In-Network
HMO In-Network
$500 $1,000
$500 $1,000
$2,500 $5,000
$1,650 $3,300
$2,000 $4,000
20% $5,500 $11,000
20% $5,500 $11,000
0% Not Applicable Not Applicable
20% Not Applicable Not Applicable
0% Not Applicable Not Applicable
$8,500 $17,000
$9,100 $18,200
$5,000 $10,000
$4,500 $9,000
$6,950 $13,900
No Charge
No Charge
No Charge
No Charge
No Charge
$30
$30
0% after deductible 20% after deductible 0% after deductible
Specialist
$50
$50
0% after deductible 20% after deductible 0% after deductible
Virtual Visit
$10
$10
0% after deductible
Behavioral Health
$25
$30
0% after deductible 20% after deductible 0% after deductible
$85
$85
0% after deductible 20% after deductible 0% after deductible
$250 Copay after deductible
$250 Copay after deductible
0% after deductible 20% after deductible 0% after deductible
Deductible Individual Family Coinsurance Coinsurance Individual Max Family Max
PriorityHSA HMO PriorityHSA HMO PriorityHSA HMO Gold G251 Gold G16 Gold G201
Annual Out of Pocket Max Individual Family Physician Office Services Preventive Care
Primary Care
$10 Copay after deductible
0% after deductible
Hospital Services
Urgent Care Emergency Room Inpatient
20% after deductible 20% after deductible 0% after deductible 20% after deductible 0% after deductible
Outpatient
20% after deductible 20% after deductible 0% after deductible 20% after deductible 0% after deductible
Diagnostic Services
$250 Copay after deductible
$250 Copay after deductible
0% after deductible 20% after deductible 0% after deductible
Labs
$35
$35
0% after deductible 20% after deductible 0% after deductible
X-Rays
$75
Imaging/CT/PET/MRI
20% after deductible 0% after deductible 20% after deductible 0% after deductible
Rehabilitative Care
Chiropractic Speech Therapy Occupational and Physical Therapy Durable Medical Equipment Prescription Drugs
$40
$40
$50 Copay after deductible $50 Copay after deductible
$50 Copay after deductible $50 Copay after deductible
0% after deductible 20% after deductible 0% after deductible 0% after deductible 20% after deductible 0% after deductible 0% after deductible 20% after deductible 0% after deductible
50% after deductible 50% after deductible 50% after deductible 50% after deductible 50% after deductible
20%/$450 max
20%/$450 max
Employee Count
$5/$35 Copay after deductible $70 Copay after deductible $90 Copay after deductible After deductible, 20% $250 max After deductible, 20% $450 max 4
Employee + Spouse Count
Generic
$5/$35
$5/$35
Preferred Brand
$80
$80
Non-Preferred Brand
$95
$95
Preferred Specialty
20%/$250 max
20%/$250 max
Non-Preferred Specialty
$5/$35 Copay after deductible $65 Copay after deductible $85 Copay after deductible After deductible, 20% $250 max After deductible, 20% $450 max 4
$5/$40 Copay after deductible $80 Copay after deductible $100 Copay after deductible After deductible, 20% $250 max After deductible, 20% $450 max 4
Employee + Children Count
Family Count
Monthly Total Premium
Total Number of Employees
$11,524.64
$13,246.16
$11,986.81
$11,989.42
$12,472.78
Annual Total Premium
$138,295.68
$158,953.92
$143,841.72
$143,873.04
$149,673.36
Current
Current
Current
Current
14.94% $20,658.24
4.01% $5,546.04
4.03% $5,577.36
8.23% $11,377.68
Compared To Annual Change (%) Annual Change ($)
Generated 5/22/2025 3:15:04 PM